Intravascular Lithotripsy (IVL)
Intravascular Lithotripsy (IVL) for Calcified Coronary Lesions in Amravati, Maharashtra
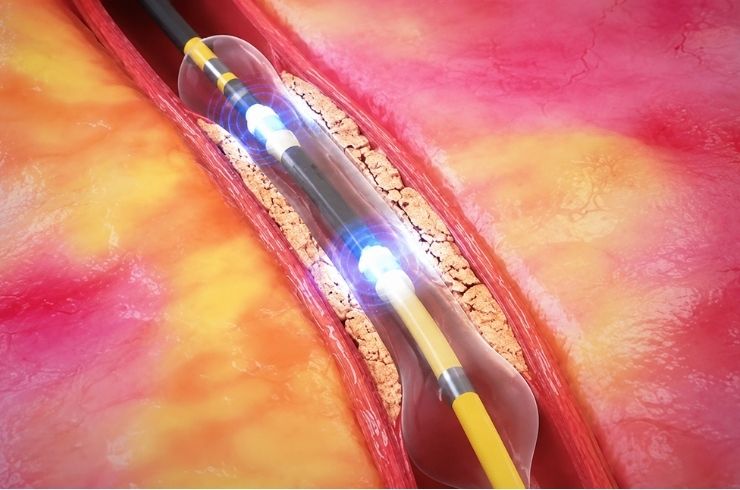
Intravascular Lithotripsy (IVL) is an advanced coronary calcium-modification technique used during PCI to treat selected heavily calcified coronary lesions. It uses controlled shockwave energy to modify calcium within the coronary artery, helping improve lesion preparation and facilitate appropriate stent expansion.
For patients seeking Intravascular Lithotripsy (IVL) in Amravati, Maharashtra, Dr. Niraj evaluates the coronary anatomy, calcium characteristics, symptoms, heart function and overall procedural risk before determining whether IVL may be appropriate.
What it is
Intravascular Lithotripsy is a catheter-based technique designed to modify calcified plaque within a coronary artery.
A specialized balloon catheter delivers controlled shockwave energy to the calcified lesion. The objective is to modify the calcium and improve the vessel’s ability to accommodate balloon expansion and subsequent stent placement.
IVL may be considered as part of a broader PCI strategy rather than as an independent treatment.
Coronary Calcium
Coronary calcium develops as part of the atherosclerotic process and can make coronary arteries rigid.
Heavily calcified lesions can create challenges during PCI, including:
- Difficulty crossing the lesion
- Difficulty expanding a balloon
- Difficulty delivering a stent
- Incomplete stent expansion
- Increased procedural complexity
Assessment of the calcium and overall coronary anatomy helps determine the most appropriate lesion-modification strategy.
Shockwave-Based Calcium Modification
IVL uses shockwave-based calcium modification within the coronary artery.
The specialized balloon is positioned across the calcified lesion and delivers controlled acoustic pressure waves. These energy pulses can modify calcium within the vessel wall while the balloon is inflated at a relatively low pressure.
After calcium modification, the vessel may become more compliant, allowing improved lesion preparation and facilitating appropriate stent deployment.
When IVL May Be Considered
IVL may be considered for selected patients with significant coronary calcification where calcium modification is required before or during PCI.
Factors that may influence the decision include:
- Severity of coronary calcium
- Calcium distribution
- Lesion characteristics
- Vessel size
- Difficulty with balloon expansion
- Difficulty with stent delivery
- Expected need for improved stent expansion
- Overall coronary anatomy
- Clinical condition and procedural risk
The decision is individualized based on coronary imaging and the patient’s overall cardiovascular condition.
Diagnosis and Calcium Assessment
Assessment may involve:
- Medical history and symptom evaluation
- ECG
- Echocardiography
- Coronary CT imaging where appropriate
- Coronary angiography
- Intravascular ultrasound (IVUS)
- Other intravascular imaging where appropriate
Intravascular imaging can provide additional information about calcium distribution, vessel dimensions and lesion characteristics that may not be fully apparent from angiography alone.
When Coronary Angiography May Be Required
Coronary angiography may be required when significant coronary disease needs detailed anatomical assessment or when PCI is being planned.
It can help determine:
- Location of the blockage
- Severity of narrowing
- Vessel anatomy
- Lesion length
- Coronary calcification
- Other affected coronary vessels
The angiographic findings, together with other clinical and imaging information, help guide the selection of an appropriate PCI strategy.
Medical Treatment
Medical treatment remains important for patients with coronary artery disease, regardless of whether IVL is performed.
Depending on individual needs, treatment may include:
- Cholesterol-lowering medication
- Antiplatelet medication when clinically indicated
- Anti-anginal medication
- Blood-pressure management
- Diabetes management
- Smoking cessation
- Weight management
- Heart-healthy dietary changes
- Appropriate physical activity
- Cardiac rehabilitation where suitable
Medical treatment may be used alone or alongside coronary revascularization.
When Intervention May Be Required
PCI may be considered when a calcified coronary lesion is clinically significant and revascularization is appropriate.
IVL may form part of the intervention when significant calcium creates challenges with lesion preparation or expected stent expansion.
Factors considered include:
- Symptoms
- Severity of coronary narrowing
- Evidence of ischaemia
- Calcium characteristics
- Coronary anatomy
- Heart function
- Overall cardiovascular risk
- Suitability of PCI compared with alternative treatment
IVL Versus Rotablation
Both IVL and rotational atherectomy (rotablation) can be used to modify calcified coronary lesions, but they use different technologies.
IVL uses controlled shockwave energy delivered through a balloon catheter to modify calcium within the vessel wall.
Rotablation uses a specialized rotating device to modify heavily calcified plaque and facilitate lesion preparation.
The choice depends on the characteristics of the lesion, vessel anatomy, calcium distribution, procedural requirements and the treating cardiologist’s assessment.
Neither technique is universally appropriate for every calcified lesion.
Combination Strategies Where Clinically Appropriate
Some complex calcified lesions may require more than one treatment technique.
Depending on the coronary anatomy and procedural findings, a strategy may involve:
- Intravascular imaging followed by IVL
- Balloon preparation followed by IVL
- Rotablation followed by balloon angioplasty
- IVL combined with other lesion-preparation techniques
- Intravascular imaging to assess the final stent result
Combined strategies are selected only when clinically appropriate and according to the individual lesion characteristics.
Role in Improving Lesion Preparation and Stent Expansion
One of the key objectives of IVL is to improve lesion preparation before stent implantation.
Effective calcium modification may help:
- Improve balloon expansion
- Facilitate stent delivery
- Improve stent expansion
- Improve stent apposition
- Reduce the likelihood of significant stent under-expansion
Intravascular imaging such as IVUS may be used before and/or after treatment in selected cases to assess the vessel and evaluate the final stent result.
Potential Benefits
In appropriately selected patients, IVL may help:
- Modify significant coronary calcium
- Improve lesion compliance
- Facilitate balloon expansion
- Support stent delivery
- Improve stent expansion
- Assist treatment of complex calcified coronary lesions
The potential benefit depends on the patient’s coronary anatomy and the characteristics of the calcified lesion.
Limitations
IVL is not suitable for every coronary lesion.
Potential limitations include:
- Lesion or vessel anatomy may not be suitable
- Difficulty delivering the IVL catheter
- Need for additional lesion-modification techniques
- Contrast exposure
- Radiation exposure
- Procedural complexity
- Possibility that PCI may not be the preferred treatment
The appropriate treatment strategy should be determined after individualized assessment.
Potential Risks
As with other invasive coronary procedures, IVL-assisted PCI carries potential risks.
These may include:
- Bleeding or bruising at the access site
- Blood-vessel injury
- Coronary complications
- Abnormal heart rhythms
- Coronary dissection or perforation
- Contrast-related kidney complications
- Heart attack
- Other procedural complications
The individual risk depends on the patient’s health, coronary anatomy and complexity of the intervention.
Treatment Alternatives
Depending on the patient’s clinical condition and coronary anatomy, alternatives may include:
- Optimal medical therapy
- Conventional balloon-based lesion preparation
- Cutting or scoring balloons where appropriate
- Rotational atherectomy
- Other PCI strategies
- Coronary artery bypass grafting (CABG)
- Heart Team evaluation
The most appropriate option depends on the severity of coronary disease, symptoms, anatomy, heart function and expected benefit.
Related Procedures
Related procedures include:
- Coronary Angiography
- Complex PCI
- Calcified Lesion PCI
- Rotablation
- Intravascular Imaging
- IVUS-Guided PCI
- Left Main PCI
- Bifurcation PCI
- CTO Angioplasty
- Multivessel PCI
- Coronary Artery Bypass Grafting (CABG)
FAQs
What is Intravascular Lithotripsy?
Intravascular Lithotripsy is a catheter-based technique that uses controlled shockwave energy to modify calcium within selected coronary lesions during PCI.
How does IVL work?
A specialized balloon catheter delivers controlled acoustic pressure waves to the calcified lesion, helping modify calcium and improve vessel compliance.
Why is IVL used for coronary calcium?
Severe calcium can make balloon expansion and stent deployment difficult. IVL may help modify the calcium and improve lesion preparation.
Is IVL the same as rotablation?
No. IVL uses shockwave energy delivered through a balloon, while rotablation uses a specialized rotating device to modify calcified plaque.
Which is better, IVL or rotablation?
Neither is universally better. The appropriate technique depends on the location, severity and characteristics of the calcium and the overall coronary anatomy.
Can IVL and rotablation be used together?
Selected complex lesions may require combined calcium-modification strategies when clinically appropriate.
Does IVL help with stent expansion?
IVL may improve lesion preparation and facilitate more adequate stent expansion in appropriately selected calcified lesions.
Can IVUS be used with IVL?
Yes. IVUS may help assess vessel size and calcium characteristics and can also assist in evaluating stent expansion and the final treatment result.
Does every calcified coronary blockage require IVL?
No. Many calcified lesions can be treated using other techniques. IVL is considered selectively based on lesion characteristics and clinical requirements.
When should I consult Dr. Niraj in Amravati?
Patients diagnosed with heavily calcified coronary disease or those advised to undergo advanced PCI can consult Dr. Niraj for assessment and individualized treatment planning.
Book an Appointment with Dr. Niraj for Intravascular Lithotripsy in Amravati
If you have been diagnosed with a heavily calcified coronary blockage or have been advised that specialized calcium modification may be required before angioplasty, Dr. Niraj can evaluate your coronary anatomy and determine whether IVL, rotablation or another treatment approach may be appropriate.